Vacutainer tubes are a common part of blood collection in clinics, hospitals, and diagnostic laboratories. Each tube connects to a compatible holder and needle, allowing its vacuum to draw blood into a sealed container. The process can make collection more controlled and reduce direct handling of the sample. A small tube, but an important one.
Different tubes serve different laboratory tests. Some contain additives that help blood clot, prevent clotting, or preserve particular components for analysis. The tube’s label and additive matter; cap colors can vary between manufacturers and regional standards. Staff should check the test requirements and tube instructions rather than rely on color alone. Details count.
Using the right tube helps laboratories receive specimens suited to their testing methods. A closed collection system can also limit spills and exposure, though it does not remove every risk. Correct identification, appropriate collection technique, and the required order of draw remain essential. Even a well-designed tube cannot fix a mislabeled specimen or poor handling.
This guide explains why vacutainer tubes are used, how their features support blood collection, and what their limits are. Their role may seem straightforward, but small errors can affect sample quality and test results. That deserves careful attention.
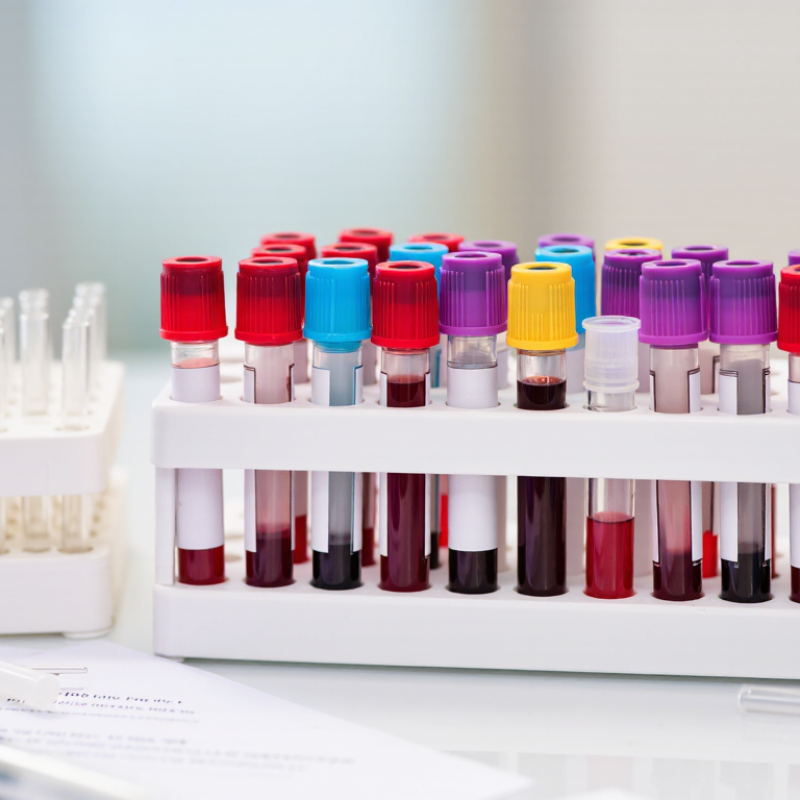
Vacutainer tubes use a preset vacuum to draw blood through the needle into a sealed tube. As blood enters, the pressure difference falls; filling stops near the tube’s intended volume. The amount is set for each tube, not guessed by the person collecting the sample. A visible fill line helps check the draw, especially for small-volume tubes. The tube’s additive and intended test also matter.
For coagulation testing, CLSI’s GP41 venous blood collection guidance specifies a 9:1 blood-to-citrate ratio. An underfilled tube can change that ratio and affect test results. The WHO’s Guidelines on Drawing Blood also stresses standardized collection and careful specimen handling. A preset volume helps consistency, but it cannot fix every problem. A loose connection, difficult vein, or early tube change may still affect the sample. Small details matter.
Tips: Let the tube fill to its marked level, and check for leakage or an incomplete draw before sending it onward. If the volume looks wrong, follow your facility’s specimen-handling procedure rather than assuming the sample is usable.
| Dimension | How It Works | Why It Matters |
|---|---|---|
| Evacuated tube | The tube is manufactured with reduced internal pressure. Once connected to a suitable blood-collection needle, the pressure difference draws blood into it. | Blood flows into a closed container without the collector needing to pull it in manually. |
| Predetermined fill volume | The vacuum is calibrated for a target fill under specified conditions. Collection stops as the pressure difference diminishes, generally near the tube’s intended fill volume. | A consistent sample volume supports laboratory testing and helps maintain the intended proportion of blood to additive. |
| Additive-to-blood ratio | Some tubes contain an anticoagulant or other additive. For example, coagulation testing tubes containing sodium citrate typically require a 9:1 ratio of blood to additive. | Filling to the specified level is especially important when an exact ratio is needed; an underfilled citrate tube can affect test results. |
| Closed collection system | The needle, holder, and tube form a closed pathway during collection when used correctly. | It helps reduce exposure to blood and lowers the chance of transferring a sample between open containers. |
| Different tube preparations | Tubes may be plain, contain a clot activator, or contain an anticoagulant such as EDTA, heparin, or citrate, depending on the intended test. | Using the correct tube helps produce the sample type required by the laboratory. Tube colors and specifications can vary, so staff should follow local procedures and tube labeling. |
| Mixing after collection | Tubes containing additives are gently inverted the number of times specified by the manufacturer or laboratory procedure. They should not be shaken vigorously. | Gentle mixing distributes the additive through the sample and helps prevent clotting in anticoagulant tubes. |
| Factors affecting the fill | Actual fill can be affected by tube size, needle or collection-set configuration, vein conditions, tube expiration or damage, and collection technique. | The target is not guaranteed in every collection. Check the fill mark and follow laboratory guidance when a tube is underfilled or otherwise unsuitable. |
Note: Follow the tube instructions and laboratory protocol for the specific test. Intended fill volumes and acceptable fill ranges vary by tube type and specification.
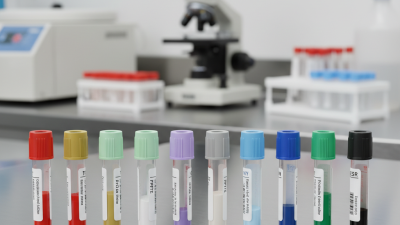
Vacutainer tubes help collect, contain, and prepare blood for specific laboratory tests. Their colored caps provide a quick visual signal about the additive inside and the specimen required. A cap is only a guide, not the final authority. Staff should confirm the tube label, test request, and local procedure before collection.
Light blue caps commonly indicate citrate tubes for coagulation studies. The blood-to-additive ratio matters, so the tube must reach its marked fill line.
Lavender or purple caps usually contain EDTA, which preserves cellular detail for hematology testing.
Serum tubes may have red or gold caps. Some contain separator gel and clot activator.
Green caps often indicate heparin tubes for selected plasma chemistry tests. Gray caps may contain additives that help preserve glucose during transport.
Color systems can differ between laboratories and regions. That detail is easy to overlook. An underfilled citrate tube, vigorous shaking, or delayed mixing can distort results. Gentle inversion is safer than shaking, while the exact number of inversions follows the tube instructions.
In a busy collection room, matching cap color with the requested test reduces preventable errors. It cannot replace patient identification and specimen checks.
Some tests require special handling, temperature control, or rapid delivery. When tube selection seems uncertain, pausing to verify the procedure is more reliable than relying on memory.
Vacutainer tubes use a controlled vacuum to draw a measured volume of blood. Their additives support specific laboratory tests. For coagulation testing, 3.2% sodium citrate tubes are especially sensitive to fill volume.
The required ratio is nine parts blood to one part citrate.
This proportion preserves the intended calcium-binding effect during transport and testing.
The ratio matters because citrate temporarily binds calcium, which clotting reactions need. When the tube is underfilled, excess citrate remains in the sample. Results may then show falsely prolonged clotting times, especially in prothrombin time or activated partial thromboplastin time testing.
A visibly short draw is not a minor defect. It can make an otherwise good specimen unreliable.
In practice, the collector should watch the blood level rather than assume the vacuum worked perfectly. Gently invert the tube according to local laboratory instructions. Do not shake it; foam and cell damage can affect sample quality.
Even experienced staff can overlook a partially filled tube during a busy collection. That is worth checking twice. The correct order of draw, a clean venipuncture, and timely delivery also support dependable results.
Still, the 9:1 ratio remains the detail that is easiest to underestimate.
Why Are Vacutainer Tubes Used in Blood Collection?
Vacutainer tubes help collect blood into a controlled, sealed container. Their additives protect samples before hematology and chemistry testing begins. The correct tube can preserve cellular detail, prevent clotting, or separate serum from blood cells. This choice affects the result. It is not merely a matter of tube color.
For hematology tests, EDTA binds calcium and limits clot formation. It helps preserve red cells, white cells, and platelets for complete blood counts. The tube must fill properly and receive gentle, immediate mixing. Too little blood can disturb the intended ratio. Vigorous shaking may cause hemolysis. Small handling mistakes can become large reporting problems.
Chemistry testing often uses tubes that produce serum or contain heparin for plasma analysis. Clot activators help serum form, while separating gel can create a barrier after centrifugation. These additives are useful, but they are not universal. Some assays may react to the additive or the separation process. Laboratory staff should follow validated procedures for inversion, clotting time, centrifugation, storage temperature, and transport. In practice, it is easy to blame the analyzer first. The tube, collection technique, or delay may deserve closer attention. Even a clear-looking sample can contain hidden interference from hemolysis, lipemia, or contamination.
Typical inversion counts help mix tube additives evenly after collection.
EDTA tubes help preserve blood cells for hematology, while citrate tubes bind calcium for coagulation testing. Heparin and fluoride-containing additives are used for selected chemistry tests; serum tubes allow blood to clot before serum is separated. Inversions gently distribute additives through the sample. Counts shown are typical guidance and may vary by tube; follow the collection tube instructions and local procedures.
Standardized evacuated tubes create a repeatable path from collection to analysis. Each tube provides a controlled volume, additive, and mixing requirement. This consistency helps laboratories compare specimens across shifts, locations, and patient visits. It also reduces avoidable variation during centrifugation, transport, and testing.
Small details matter. An underfilled citrate tube can distort coagulation results, while poor mixing may leave microclots.
The World Health Organization’s Guidelines on Drawing Blood stresses correct tube selection, patient identification, collection order, and gentle inversion. Clinical Chemistry and Laboratory Medicine reviews report that preanalytical problems may represent 46–68% of laboratory errors. Standardized tubes cannot remove every risk, but they support clearer procedures.
A visible fill line helps staff identify inadequate volume. Color-coded closures also support faster recognition, although color systems must follow local laboratory policy.
In practice, safe handling depends on more than the tube itself. Staff still need verified training, clean technique, timely transport, and documented storage conditions. ISO 15189:2022 also emphasizes controlled pre-examination processes and traceability.
A correct tube can still produce a poor specimen. That is the uncomfortable part. Human judgment remains necessary, especially when veins are difficult, collection is urgent, or the patient’s condition changes. Consistency improves safety, but it should never replace careful observation.